
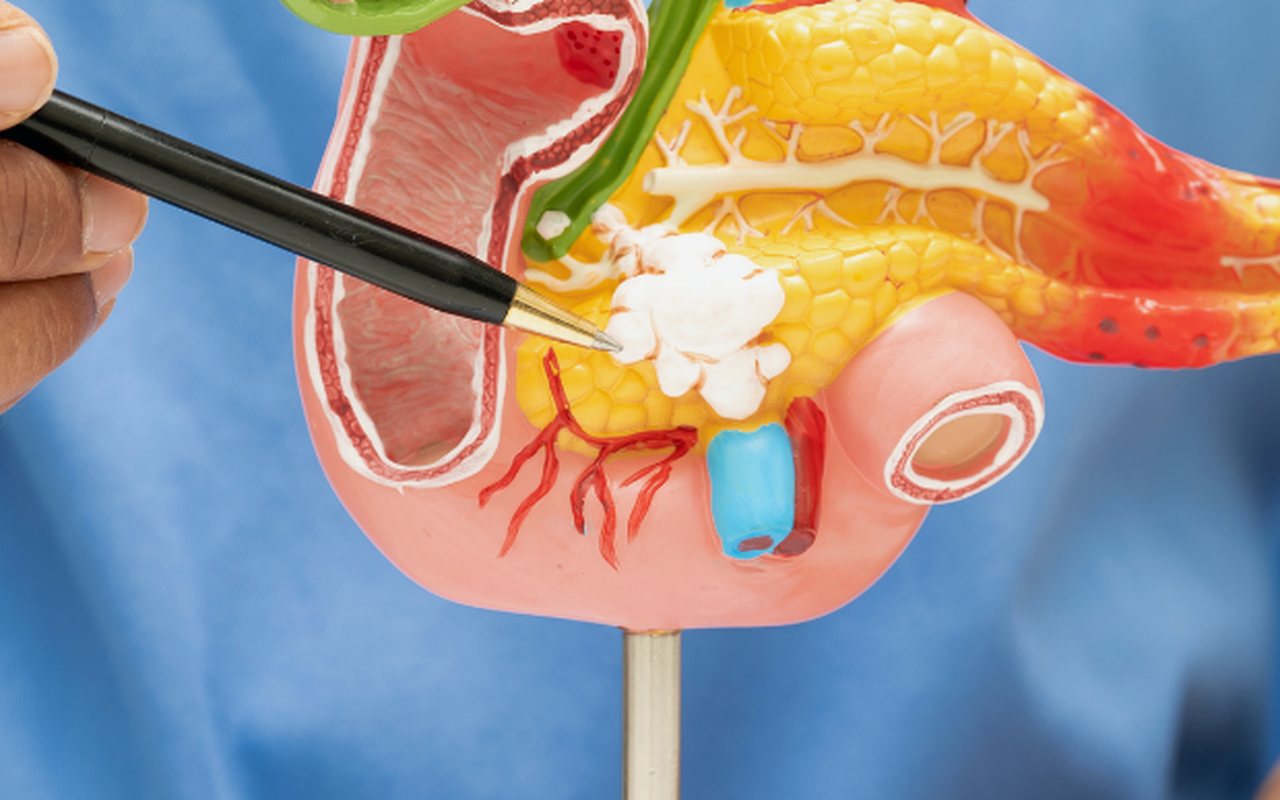
Gallbladder surgery
The gallbladder comes out, not just the stones. Laparoscopic in the great majority of cases, with discharge the next day.
See the procedure
Twenty procedures across general, gastrointestinal, laparoscopic and bariatric surgery, described one by one.
These are the twenty procedures performed by Dr. Ari Salgado, each with its own page: what the operation involves, when it is indicated, the techniques used and the questions patients actually ask about it. None of them is decided from a website — every indication is decided on your own studies and your own physical examination.
The gallbladder comes out, not just the stones. Laparoscopic in the great majority of cases, with discharge the next day.
See the procedure
The wall defect is closed and reinforced with mesh. A truss does not cure a hernia: it only hides it.
See the procedure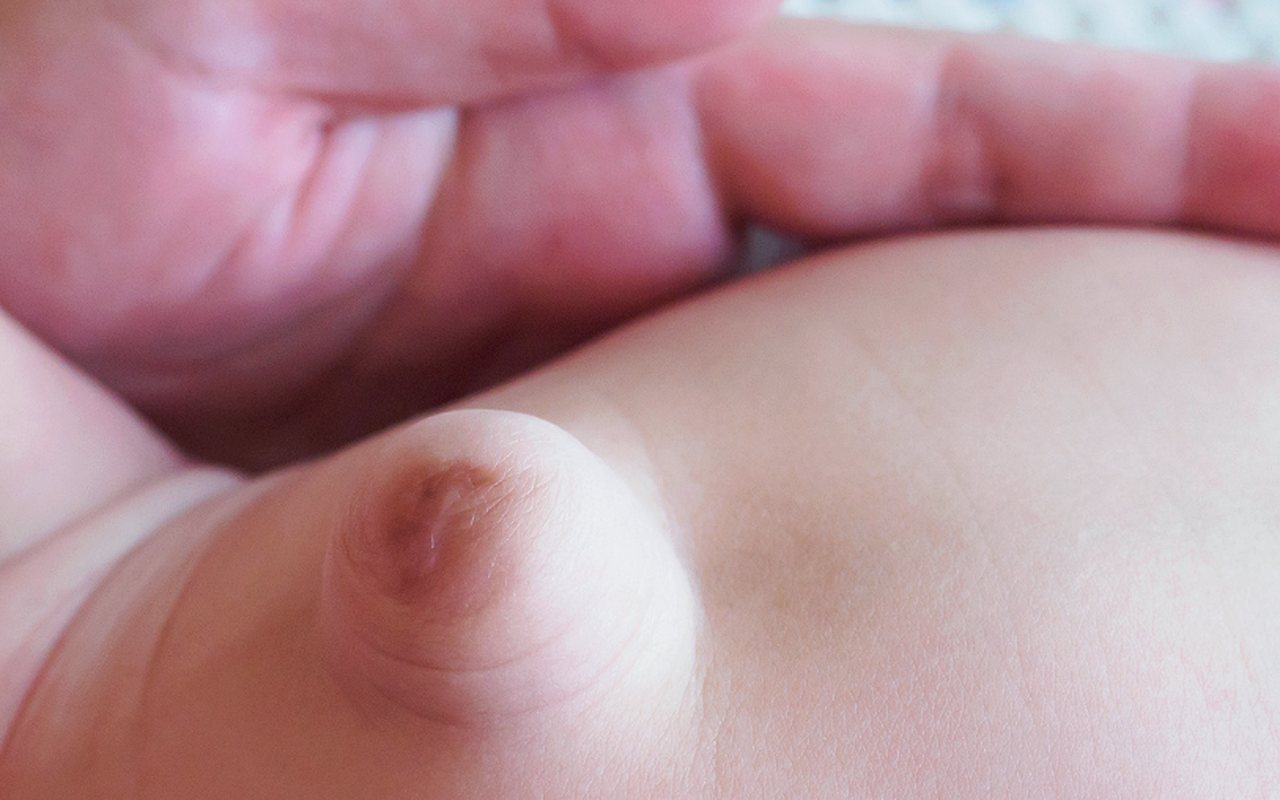
The navel is the weakest point of the midline. The defect is closed and reinforced when size demands it.
See the procedure
An incisional hernia comes out through the scar of a previous operation. It is repaired with mesh and prior planning.
See the procedure
The stomach is returned to the abdomen, the hiatus is closed and an anti-reflux valve is built from the gastric fundus itself.
See the procedure
Appendicitis does not wait. It is operated on within hours, through three small incisions, with discharge usually in 24 to 48 hours.
See the procedure
Not every haemorrhoid needs surgery. The ones that do bleed repeatedly, prolapse and stay out, or thrombose.
See the procedure
The gland is removed, whole or one lobe, according to the diagnosis. The voice and the parathyroids are the technical priority.
See the procedure
It comes out whole, with its capsule, and goes to pathology. Taking it out in pieces is how it comes back.
See the procedure
Without a histological diagnosis there is no correct treatment. The biopsy answers the question: what exactly is this.
See the procedure
In during the morning, home in the afternoon. It requires selecting both patient and procedure — it is not for every case.
See the procedure
There are abdominal presentations measured in hours. This is the list of the ones that cannot wait for Monday's appointment.
See the procedure
A portion of the stomach is removed and a sleeve remains. Less volume, early satiety, and a nutrition plan that goes with it.
See the procedure
It restricts and also changes the path food takes. It is the procedure with the strongest effect on diabetes and on reflux.
See the procedure
An adjustable ring on the upper stomach. Nothing is cut or rerouted: it is the reversible bariatric procedure.
See the procedure
The diseased segment is resected and continuity restored. Where there is cancer, margins and lymphadenectomy rule.
See the procedure
A tumour is not removed to find out what it was. It is investigated, the margin is planned, and then it is operated on.
See the procedure
A wound open for weeks has a cause. Treatment starts by finding it, not by changing the dressing.
See the procedure
The ulcer is treated with medication; its complication is operated on. A gastric tumour is operated on with oncological criteria.
See the procedure
Reflux is operated on for its consequences, not for its name. The decision is made with endoscopy and functional studies.
See the procedureNo surprises: what happens at each stage, what will be asked of you, and at which point the decision to operate — or not to — is made.
Call (664) 108-6258 or send the form. You are told which studies to bring, and urgent cases are prioritised the same day.
How it started, what makes it worse, what has already been tried, and what else you live with. Half the surgical diagnosis comes from here.
Abdomen, groins, previous scars, neck and anal region as the case requires. This is what decides whether an imaging finding really explains your symptom.
Ultrasound, CT, endoscopy and labs are reviewed on screen with you present, and you are told what is there and what is not.
Whether there is a surgical indication, which technique, and what the alternatives are. Surgical risk, costs and prognosis are handed over in writing.
Hospital scheduling, surgery, discharge with clear instructions, and follow-up visits until the episode is closed.
One consultation with your ultrasound or CT in hand is worth more than ten internet searches. Book by phone or through the form and you will be told what is there, what it means and what your options are.